

Audio
Video
Transcript available via YouTube
Is it ready for prime time?
Cut through the hype of Multi-Cancer Early Detection (MCED) tests and learn how to counsel patients on the real-world utility, false-positive risks, and the “stage shift” debate of these emerging blood assays. We are joined by world-renowned oncologist Dr. Margaret Tempero, UCSF Cancer Early Detection and Interception, to discuss whether these tests are truly ready for clinical prime time.
Claim CME for this episode at curbsiders.vcuhealth.org!
Patreon | Episodes | Subscribe | Spotify | YouTube | Newsletter | Contact | Swag! | CME
Show Segments
- 00:00 Introduction
- 01:57 Current Cancer Screening Programs
- 06:05 Emerging Blood-Based Cancer Tests
- 11:55 Test Characteristics and Limitations
- 18:05 Practical Considerations for Patients
- 25:33 Direct-to-Consumer Testing/Whole Body MRIs
- 36:46 Navigating Positive Test Results
- 45:10 Anxiety and Patient Education
- 47:08 Future Directions in Cancer Screening
- Outro
Disclosures
Dr. Tempero reports the following financial relationships:
Grail (research support), Global Bio Access Fund (Advisor), Bristol Myers Squibb (Membership on Advisory Committees or Review Panels, Board Membership, etc.), Astra Zeneca (Membership on Advisory Committees or Review Panels, Board Membership, etc), Immunovia (Membership on Advisory Committees or Review Panels, Board Membership, etc.), Merck (advisory committee), Renovo Rx (advisory committee), Urogen (Advisor). Financial relationships have not ended.
The Curbsiders report no relevant financial disclosures.
CME Partner: VCU Health CE

The Curbsiders are partnering with VCU Health Continuing Education to offer continuing education credits for physicians and other healthcare professionals. Visit curbsiders.vcuhealth.org and search for this episode to claim credit.
Multi Cancer Early Detection Pearls
1. MCED ≠ screening replacement. Multi-cancer early detection (MCED) tests should not replace USPSTF-recommended screening (breast, colorectal, cervical, lung ± prostate). They are, at best, complementary, and skipping proven screening for a blood test is a net harm.
2. Earlier detection ≠ better outcomes (yet). The central question is mortality benefit- not just finding cancer earlier. So far, MCEDs have not demonstrated a clear “stage shift” or survival benefit, and that evidence may take years to emerge.
3. False positives occur and are consequential. Only ~1–2% of tests are positive, but a significant number of individuals with a positive Galleri signal did not ultimately have an identifiable cancer diagnosis (38.4% false discovery rate = 100% minus PPV of 61.6%). Downstream effects include anxiety, imaging, radiation exposure, and invasive procedures.
4. Test performance is uneven (and biased toward later-stage disease). Sensitivity varies widely by cancer type, and many early-stage cancers are missed. Some tumors (e.g., pancreatic) are “poor shedders,” meaning a negative test does not rule out cancer.
5. Shared decision-making is essential. Patients should understand the trade-offs: uncertain benefit, real harms, out-of-pocket cost, and lack of FDA approval for most tests balanced with an opportunity to potentially detect cancers that we currently do not have routine screening for. Framing expectations upfront is key to avoiding misinterpretation of results.
Multi Cancer Early Detection Testing Notes
Current Cancer Screening
There are hundreds of cancer types, often grouped into ~20 categories by organ system. The U.S. Preventive Services Task Force currently recommends routine screening for four cancers (breast, colorectal, cervical, and lung), with a conditional recommendation for prostate cancer- leaving the majority of cancers without established screening pathways (Lynge 2026). This means many cancers are not detected by screening, and only at later stages when they are more difficult to treat.
Multi-Cancer Early Detection (MCED) Testing
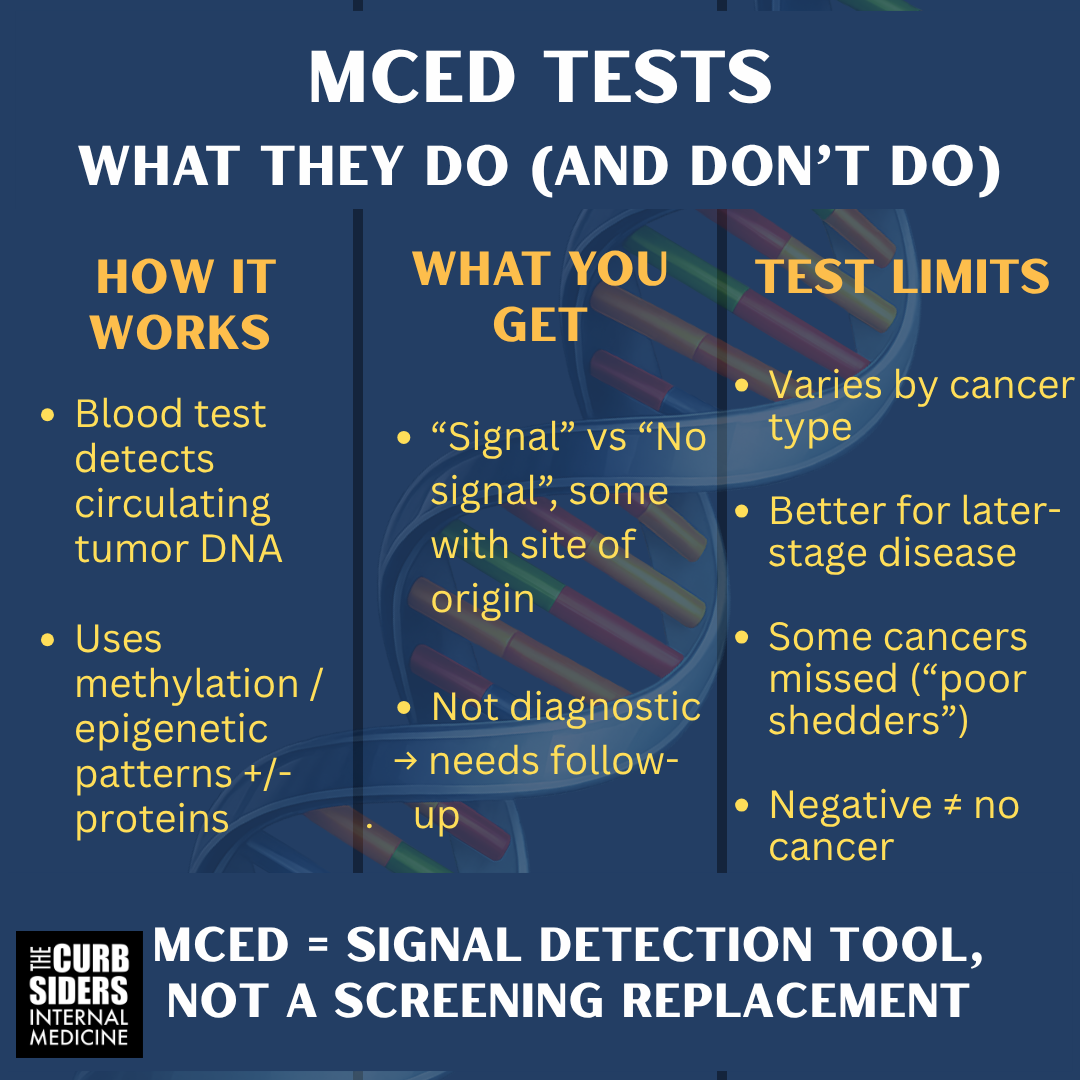
Multi-cancer detection tests emerged from advances in liquid biopsy in cancer diagnostics. These blood tests detect circulating tumor DNA (ctDNA)- small fragments of cancer-derived DNA in the bloodstream were used to identify cancer genetic mutations, early cancer recurrences, or remission status. Now with advanced technologies cancer markers can be identified through changes in methylation, gene expression, or other epigenetic markers. Additional biomarkers, such as cytokines, metabolites, and tumor-associated proteins, may further enhance cancer detection in the future (Rubenstein 2024).
The goal is early cancer detection at a curable stage. However, performance varies by cancer type and stage, with later-stage cancers more readily detected than early-stage disease due to increased shedding into the blood stream.
Galleri test by Grail
The Galleri test analyzes cell-free DNA methylation patterns and can often predict the tissue of origin if a cancer signal is detected. Detection varies significantly across cancers; for example, pancreatic cancer is a “poor shedder,” with only ~20% of even metastatic cases having ctDNA in the blood (Keane 2025). In contrast, some cancers (e.g., head and neck) may be identified earlier, though comprehensive data are still emerging. Galleri currently has the most published evidence among MCED tests.
- In the Pathfinder 2 study, despite a reported positive predictive value of 61.6%, there was a false discovery rate of 38.4% because 83 out of the 216 cases with cancer signal detected did not have an identifiable cancer after 12 months follow up (Lippi 2026).
- The NHS-Galleri randomized controlled trial did not meet their primary endpoint of a meaningful “stage shift” (i.e., reduction in stage 3-4 cancers with increased early-stage detection). Results of this have been presented at but not published in peer reviewed journals. They did show a reduction in stage 4 cancers diagnosed and an increase in stage 1 and 2 cancers. While earlier detection is promising (ie showing a stage shift), some experts argue that a demonstrated mortality benefit remains the gold standard- though this may take decades to establish.
- REACH study is currently recruiting in the US looking at an older population of MediCare patients.
Other blood based MCED Tests
Additional MCED tests are entering the market, but have limited published data. These may use different combinations of signals and have differing sensitivity and specificity (Kahwati 2025). Exact Sciences offers a commercially available test, Cancerguard, that combines cell-free DNA and protein markers, though it does not localize the cancer signal. At present, the *Shield test (for colon cancer screening only) is the only FDA-approved blood-based cancer screening test; other MCDTs are not FDA-approved and are typically not covered by insurance. All require a clinician’s order (directly or via affiliated telehealth services).
*Correction (added 25 May 2026): The Shield test is made by Guardant. On the episode we mistakenly attributed Shield to Exact Sciences.
Limitations and Uncertainties
Interpreting test performance is challenging due to the lack of gold-standard for diagnosing many cancers. Approximately 1–2% of MCED tests return positive (Matrana 2025), with significant false-positive rates (Rubenstein 2024). Importantly, detecting indolent cancers (e.g., low-risk prostate or thyroid cancers) may not improve outcomes. There is limited published data about detection rates for specific cancers. MCDTs should not replace guideline-recommended screenings.
False positives can lead to anxiety, unnecessary imaging, and invasive procedures.

Diagnostic Follow-Up
When MCED test results are positive:
- Galleri may provide a predicted tissue of origin, helping guide evaluation.
- Non-localizing tests may require broader workup, often including whole-body PET/CT imaging.
- If initial follow-up is unrevealing, some experts like Dr Tempero recommend repeating MCED testing in 6 months.
Guidelines for standardized follow-up are in development, with anticipated publication in 2026.
Screening Whole Body MRIs
Whole-body MRI is not recommended for average-risk individuals due to lack of evidence for improved outcomes and concerns about variable quality in direct-to-consumer settings (Dai 2026). Direct to consumer MRIs performed at commercial sites are often performed on lower quality machines and may have less quality reads compared to imaging at a major medical center.
Patients with high-risk genetic syndromes (e.g., Li-Fraumeni syndrome) are currently recommended to undergo whole-body MRI surveillance (Achatz 2025). Dr Tempero feels MCED tests may eventually play a role in these populations if cost and performance improve.
Key Considerations
Cancer screening must be understood in the context of disease prevalence and incidence. A negative test does not rule out cancer, and new cancers may develop over time- raising questions about optimal screening intervals if these tests are validated. Large studies, such as the Vanguard trial, aim to better define the role of MCED tests in population screening.
Bottom Line
Blood-based multi cancer screening is an exciting and rapidly evolving field, but significant limitations remain (Ebbert 2025). These tests may offer earlier detection for some cancers, but false positives, uncertain clinical impact, and lack of mortality data are important considerations. For now, they should be viewed as complementary- not replacements- for established screening, and patients should be counseled carefully on potential benefits and harms. False positives can be anxiety provoking (Naudald 2025) and can lead to unnecessary radiation or procedures.
Dr Tempero hopes that in the coming years as data accumulates and is shared, we will understand better what cancers these tests are good at detecting. She is hopeful we can refine who best benefits from these tests, ie for example maybe only people over age 65 or patients at increased risk of head and neck cancer (ie hx of nicotine/alcohol use).
Goal
Listeners will be better able to integrate current evidence regarding multi-cancer early detection (MCED) tests into patient-centered counseling and clinical decision-making for asymptomatic adults.
Learning objectives
After listening to this episode listeners will…
- Compare the effectiveness and scope of current USPSTF-recommended cancer screening programs with emerging multi-cancer early detection (MCED) blood tests.
- Interpret the test characteristics of commercially available MCED assays and appraise the limitations of existing evidence.
- Apply shared decision-making strategies to counsel asymptomatic adults about the risks, benefits, uncertainties, and downstream implications of both negative and positive MCED test results.
Citation
Heublein M, Tempero M, Williams PN, Watto MF. “#525 MultiCancer Early Detection
Is it ready for prime time?” The Curbsiders Internal Medicine Podcast. thecurbsiders.com/category/curbsiders-podcast May 18, 2026.
Episode Sponsors
Episode Credits
Producer, Writer, Show Notes, Infographic, Cover Art: Molly Heublein MD
Hosts: Matthew Watto MD, FACP; Paul Williams MD, FACP
Reviewer: Sai S Achi MD,MBA,FACP
Showrunners: Matthew Watto MD, FACP; Paul Williams MD, FACP
Technical Production: PodPaste
Guest: Margaret Tempero, MD
CME Partner

The Curbsiders are partnering with VCU Health Continuing Education to offer continuing education credits for physicians and other healthcare professionals. Visit curbsiders.vcuhealth.org and search for this episode to claim credit.
Contact Us
Got feedback? Suggest a Curbsiders topic. Recommend a guest. Tell us what you think.
We love hearing from you.
Join our Patreon!

Yes, you can now join our exclusive community of core faculty at Kashlak Memorial Hospital along with all the perks:
- Bundle & Save with the top CME tier!
- All episodes Ad-Free, including the entire back catalog!
- Twice-monthly bonus episodes: Ask me Anything (AMA) with Matt & Paul, Recaps, and more!
- Access to Kashlak's Discord Server!
- Advance Notice of Curbsiders Events!
- Exclusive Curbsiders' Merch!
