

Audio
Video
Transcript available via YouTube
All About Disorders of Gut-Brain Interaction
Master disorders of gut–brain interaction. Learn how Rome V changes the diagnosis of IBS and other DGBIs, how to approach chronic diarrhea and the microbiome, and how to choose targeted treatments for bloating, pain, and vomiting. We’re joined by Dr. Xiao Jing (Iris) Wang, a gastroenterologist and expert in disorders of gut–brain interaction.
Claim CME for this episode at curbsiders.vcuhealth.org!
Patreon | Episodes | Subscribe | Spotify | YouTube | Newsletter | Contact | Swag! | CME
Show Segments
- Intro
- Updates to Rome V Criteria
- Microbiome Information
- Evaluation and Management of Chronic Diarrhea
- Abelchia
- Abdominophrenic Dyssynergia
- Key Takeaways
- Outro
Disclosures
Dr. Wang reports no relevant financial disclosures. The Curbsiders report no relevant financial disclosures.
More Than a Gut Feeling – DGBIs with Dr. Iris Wang Pearls
- Diagnose DGBI positively – do not make it a diagnosis of exclusion.
- Dietary fiber and a Mediterranean diet can help support a healthy microbiome.
- As there is no standardized “ideal” microbiome, microbiome testing is currently not clinically helpful.
- For individuals presenting with chronic constipation and/or diarrhea, it is important to identify the alarm / red flag features that would require invasive workup.
- There are many non-pharmacologic options to help individuals with IBS manage their symptoms.
- Abelchia, or the inability to belch, is a real, treatable condition.
- Abdominophrenic dyssynergia is characterized by visible distention without an increase in luminal gas.
More Than a Gut Feeling – DGBIs with Dr. Iris Wang – Notes
Disorders of Gut–Brain Interaction (DGBI) and the Rome V Framework
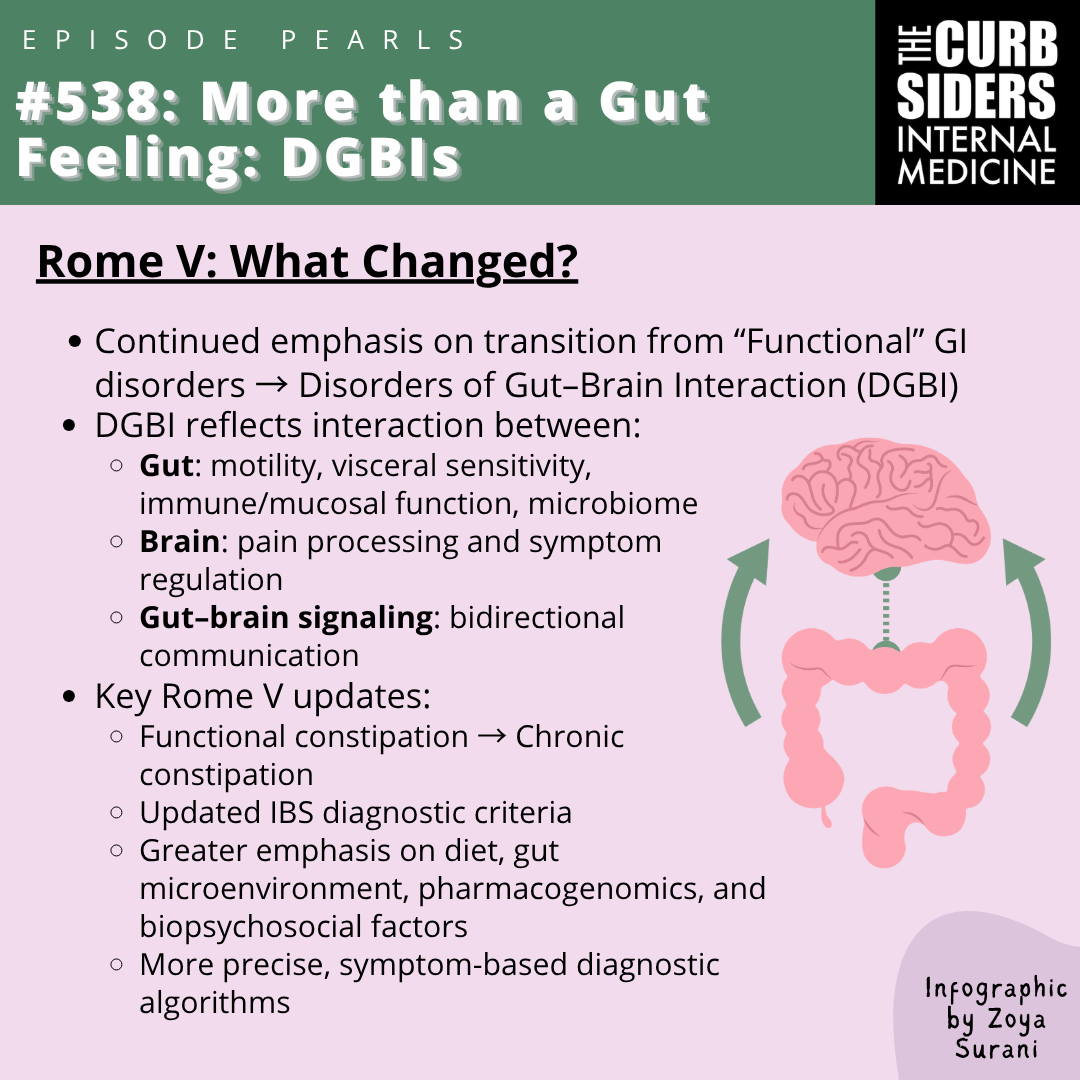
A central theme of Rome V is to continue the move away from the term “functional” GI disorders toward the concept of disorders of gut–brain interaction. These conditions reflect some combination of a primary gut problem (motility disturbance, visceral hypersensitivity, immune/mucosal dysfunction, or altered gut microbiota), altered central nervous system processing and management of pain, and the bidirectional interaction between the gut and CNS (Drossman et al., 2026).
The microbes residing in the gut modulate hormone production, participate in food processing, and shift the balance between pro-inflammatory and anti-inflammatory states, and many of the same neurotransmitters act on both the enteric and central nervous systems.
The Rome V process updated definitions based on new literature, incorporated the roles of diet, the gut microenvironment, pharmacogenomics, and biopsychosocial and cross-cultural factors, deliberately reduced imprecise terminology, and generated updated diagnostic algorithms.
Key Rome V Changes in the Bowel/Gastroduodenal Disorders
Notable changes in Rome V criteria per Dr. Wang include:
- Functional constipation renamed chronic constipation.
- Functional dyspepsia emphasis on distinguishing pain unrelated to eating (Epigastric Pain syndrome) from postprandial-related symptoms (Postprandial Distress Syndrome), with recognition of a postprandial epigastric pain syndrome (referenced in The Curbsiders episode #334 with Dr. Iris Wang).
- IBS criteria revisions: “discomfort” was added back, so patients may present with pain or discomfort (but symptoms should not be continuous and should not be related only to menses); the qualifying frequency shifted to roughly three episodes per month rather than weekly; IBS can be diagnosed at three months, with a caveat that a shorter duration is acceptable when suspicion is high, though at least ~8 weeks is needed to reasonably exclude other diagnoses; and symptoms should be sufficiently bothersome to prompt care or interfere with daily quality of life.
The Microbiome
Certain organisms are pro-inflammatory and others anti-inflammatory; gut health reflects the overall combination of resident microbes and the balance between these states rather than any single species.
While we know that a diverse population of microbes rich in antiinflammatory bacteria is good, the optimal microbiome composition for a given individual is unknown, and there is no gold standard against which an individual’s microbiome can be judged.
Dietary patterns are the most evidence based way to impact the microbiome. High-fiber, Mediterranean-style diets rich in fiber and antioxidants, fermented foods, and yogurt with live cultures can grow and maintain a healthy microbiome. In particular, dietary fiber from whole grains, resistant starch, and fruit supports a diverse microbiome.
Favoring foods that nourish a patient’s existing microbes is generally preferable to routine probiotic supplements, which introduce only specific species and do not foster natural diversity. Dr. Wang shares that “[With probiotics/supplements], it’s almost like you’re selectively planting plants as opposed to enriching the soil. Eating fiber is almost like using a fertilizer to enrich a garden.”
A low–processed-food diet and avoidance of unnecessary antibiotics also support the microbiome.
Evaluation of Chronic Diarrhea
Per Dr. Wang, a focused history for a patient presenting with chronic diarrhea should establish:
- Family history of colorectal cancer or advanced polyps in a first-degree relative, which may warrant shifting the age of screening colonoscopy.
- NSAID use — frequency and amount.
- Dietary triggers and overall diet balance.
- International travel and the timeline of symptom onset.
- Gynecologic history in women — menorrhagia, dysmenorrhea, and possible endometriosis, increasingly recognized as associated with IBS-type GI symptoms.
- Family history of endocrine dysfunction and GI symptoms in relatives.
- Associated pain/fatigue suggesting a fibromyalgia-type picture.
- Mood — anxiety or depression, including symptoms triggered by the GI illness.
- Atopic history — asthma, allergies, eczema.
- Alarm features — nocturnal diarrhea, weight loss, and rectal bleeding.
A differential may include IBS, lactose intolerance, colorectal cancer, inflammatory bowel disease, chronic infections, and less commonly endometriosis, eosinophilic disease, and other rarer conditions.
Counseling and Workup for Chronic Diarrhea Without Alarm Features
Sharing the Rome V criteria and diagnostic algorithm with the patient and family — walking through the criteria they meet and the recommended workup together — reinforces confidence in the diagnosis.
In a young patient with no alarm features, a limited workup (e.g., fecal calprotectin and celiac serologies) is appropriate to exclude inflammatory and other organic disease.
Guidelines do not mandate colonoscopy in this setting, though individual thresholds vary, as Dr. Wang mentions, since clinically significant polyps are not rare even in patients in their 30s. When colonoscopy is not indicated, it is reasonable to explain that yield is low, that it is invasive (bowel prep, anesthesia), and that anesthesia and prep can transiently alter the microbiome.
Microbiome testing is not recommended: it has not been validated against any clinical outcome, there is no gold standard for a “normal” microbiome, and results may be misinterpreted — potentially leading to unnecessary antibiotics or dietary restriction.

Management of IBS
The Rome V bowel disorder framework and current guidelines support a stepped approach based on severity:
- Mild symptoms — diet and lifestyle. General measures include regular mealtimes, adequate fluid intake, limiting caffeine, alcohol, and carbonated beverages, and adjusting fiber (favoring soluble fiber). Attention to sleep, stress management, physical activity, and mind–body approaches (meditation, yoga, breathwork to regulate vagal tone) is appropriate. Gut-directed hypnotherapy has a growing evidence base, and some patients use acupuncture. When symptoms persist, a dietitian-supervised low-FODMAP diet improves symptoms in a substantial proportion of patients, followed by structured reintroduction to tolerance to avoid long-term dysbiosis.
- Moderate symptoms — pharmacologic therapy targeted to the predominant symptom.
- Severe symptoms — central neuromodulators, often in conjunction with brain–gut behavioral therapy.
Brain–gut behavioral therapies are an important adjunct, and the greater the burden of psychosocial comorbidity in the patient, the more they may benefit from in-person or telehealth care with an actual GI psychologist rather than a self-directed app.
Digital and telehealth resources noted by Dr. Wang include the Nerva app (gut-directed hypnosis/CBT, from Mindset Health; subscription covered by Medicaid), Abyle Health (brain-gut behavior therapies, nutrition-focused guidance; insurance covered and allows back and forth of communication with the referring provider), Lin Health (brain-gut behavior therapy, access to a pain coach; insurance covered and allows back and forth of communication with the referring provider), and virtual GI-psychology groups. STW5 (a preparation containing peppermint, chamomile, and caraway) was also mentioned as a supplement option (Grundman et al., 2018).
Additional non-pharmacologic IBS treatments are described in this article (Wang, Thankur, and Shapiro, 2024).
Vomiting in Rome V
Within gastroduodenal disorders, the first step is to determine whether the presentation is pain-predominant or nausea-and-vomiting–predominant, as this now determines which algorithm to follow. In pain-predominant presentations, upper endoscopy is incorporated when alarm features or risk factors are present. Gastroparesis is characteristically a nausea-predominant rather than pain-predominant condition. Additional discussion of vomiting disorders in DGBI can be found in episode #334 of The Curbsiders (Gibson et al., 2022).
Inability to Belch (Retrograde Cricopharyngeus Dysfunction / “Abelchia”)
This condition, popularized on social media and also termed retrograde cricopharyngeus dysfunction (R-CPD), is characterized by the inability to belch: the upper esophageal sphincter fails to relax to vent gas that enters the esophagus, a pattern that can be seen on manometric studies.
Typical symptoms include neck/throat gurgling, bloating, abdominal pain, chest discomfort, excessive flatulence, and hiccups.
Most affected patients report an inability to belch since childhood; the overall epidemiology remains undefined.
Treatment is botulinum toxin injection into the cricopharyngeus/upper esophageal sphincter by ENT specialists (Karagama 2021). Dr. Wang shares that these treatments are not permanent, but can last around six months in most patients.
This diagnosis is distinct from post-Nissen fundoplication patients, in whom gas is trapped below the lower esophageal sphincter rather than at the UES.
Abdominophrenic Dyssynergia (APD)
APD is an abnormal viscerosomatic reflex causing visible distention with food intake: instead of the normal response (anterior abdominal wall contraction and diaphragmatic relaxation), the diaphragm paradoxically contracts (descends) and the abdominal wall relaxes, pushing the contents forward and producing marked distention.
Classically, patients report waking with flat abdomens and comfortable, then developing visible distention (“looking pregnant”) after even a sip of water or any meal.
On imaging, the visible distention occurs without a meaningful increase in intraluminal gas (roughly 50 ccs, insufficient to explain the distention), and often coexists with visceral hypersensitivity.
Dr. Wang shared that Dr. Apzpiroz’s group in Barcelona, which has studied the condition for many years, has characterized the abnormal diaphragmatic movement using thoracoabdominal EMG. Their work has shown patients recruiting intercostal muscles to breathe because the diaphragm is already contracted — hence the frequent complaint of being so distended they “can’t breathe” (Barbra et al., 2024; Damianos et al., 2022; Moshiree et al., 2023).
Before diagnosing APD, exclude alarm features including an increase in belching/flatulence, a change in gas odor, and confirm the absence of a clear food trigger, gastroparesis, constipation, and pelvic floor dysfunction.
Treatment is behavioral, targeting the physiology of breathing: thoracoabdominal wall motion–guided biofeedback to retrain diaphragmatic excursion and also regulate vagal tone.

Main Takeaway
For the DGBI population, more precise, symptom-based classification under Rome V allows better listening to patient symptoms, narrower diagnoses, and more targeted, patient-centered treatment.
Links


- Boo Can’t Poo (book)
- Boo’s Big Achoo! (book)
Goal
Listeners will develop a practical framework for recognizing, evaluating, and managing common Disorders of Gut-Bran Interaction.
Learning objectives
After listening to this episode listeners will…
- Define Disorders of Gut-Brain Interaction (DGBIs) and explain the shift away from the term “functional gastrointestinal disorders”.
- Apply the Rome V criteria to guide diagnostic workup for patients with DGBIs.
- Recognize, evaluate, and manage irritable bowel syndrome, abelchia, and abdominophrenic dyssynergia.
- Outline an approach to differentiate pain-predominant from nausea/vomiting-predominant DGBIs.
Citation
Surani Z, Wang XJ, Williams PN, Watto MF. “#538 More Than a Gut Feeling – DGBIs
with Dr. Iris Wang”. The Curbsiders Internal Medicine Podcast. thecurbsiders.com/category/curbsiders-podcast August 31, 2026.
Episode Sponsors
Panacea
Visit panacea.legal/curb to schedule your free consultation.
UpToDate
For a limited time, listeners can get 10% off UpToDate packages with code CURB at store.uptodate.com
FIGS
Curbsiders listeners can get 15% off. Just go to WearFIGS.com and use code FIGSRX.
MasterClass
Get at least 15% off any annual membership at MASTERCLASS.com/CURB
Episode Credits
Written and Produced by: Zoya Surani
Show Notes, Infographic, Cover Art by: Zoya Surani
Hosts: Matthew Watto MD, FACP; Paul Williams MD, FACP
Reviewer: Sai Achi MD, MBA, FACP
Showrunners: Matthew Watto MD, FACP; Paul Williams MD, FACP
Technical Production: PodPaste
Guest: Dr. Xiao Jing (Iris) Wang
CME Partner

The Curbsiders are partnering with VCU Health Continuing Education to offer continuing education credits for physicians and other healthcare professionals. Visit curbsiders.vcuhealth.org and search for this episode to claim credit.
Contact Us
Got feedback? Suggest a Curbsiders topic. Recommend a guest. Tell us what you think.
We love hearing from you.
Join our Patreon!

Yes, you can now join our exclusive community of core faculty at Kashlak Memorial Hospital along with all the perks:
- Bundle & Save with the top CME tier!
- All episodes Ad-Free, including the entire back catalog!
- Twice-monthly bonus episodes: Ask me Anything (AMA) with Matt & Paul, Recaps, and more!
- Access to Kashlak's Discord Server!
- Advance Notice of Curbsiders Events!
- Exclusive Curbsiders' Merch!
