

Audio
Video
Transcript available via YouTube
2024 ACC/AHA guideline update, including biomarker testing, MINS, and other consulting tips
Master perioperative medicine! Learn when to hold ACE inhibitors, how to manage OSA without delaying surgery, and why “NPO after midnight” is outdated. We’re joined by Dr. Avital O’Glasser, our Chief of Perioperative Medicine!
Claim CME for this episode at curbsiders.vcuhealth.org!
Patreon | Episodes | Subscribe | Spotify | YouTube | Newsletter | Contact | Swag! | CME
Show Segments
- Intro
- Case
- Preoperative Assessment & Consulting Tips
- Risk Calculators
- Frailty
- Pulmonary Considerations
- Cardiovascular Meds & BP Management
- NPO: Why Are We Still Doing This?
- Biomarkers & Postoperative Risk
- MINS
- Outro
Perioperative Pearls:
- Each cardiac risk calculator has a threshold for which it denotes elevated risk; Dr. O’Glasser prefers the MICA (Gupta) which denotes elevated risk at 1%. Look at what the calculator is measuring, for the MICA it is myocardial infarction or cardiac arrest (MICA). Patients without elevated risk, or those with elevated risk but adequate functional status can often proceed straight to surgery.
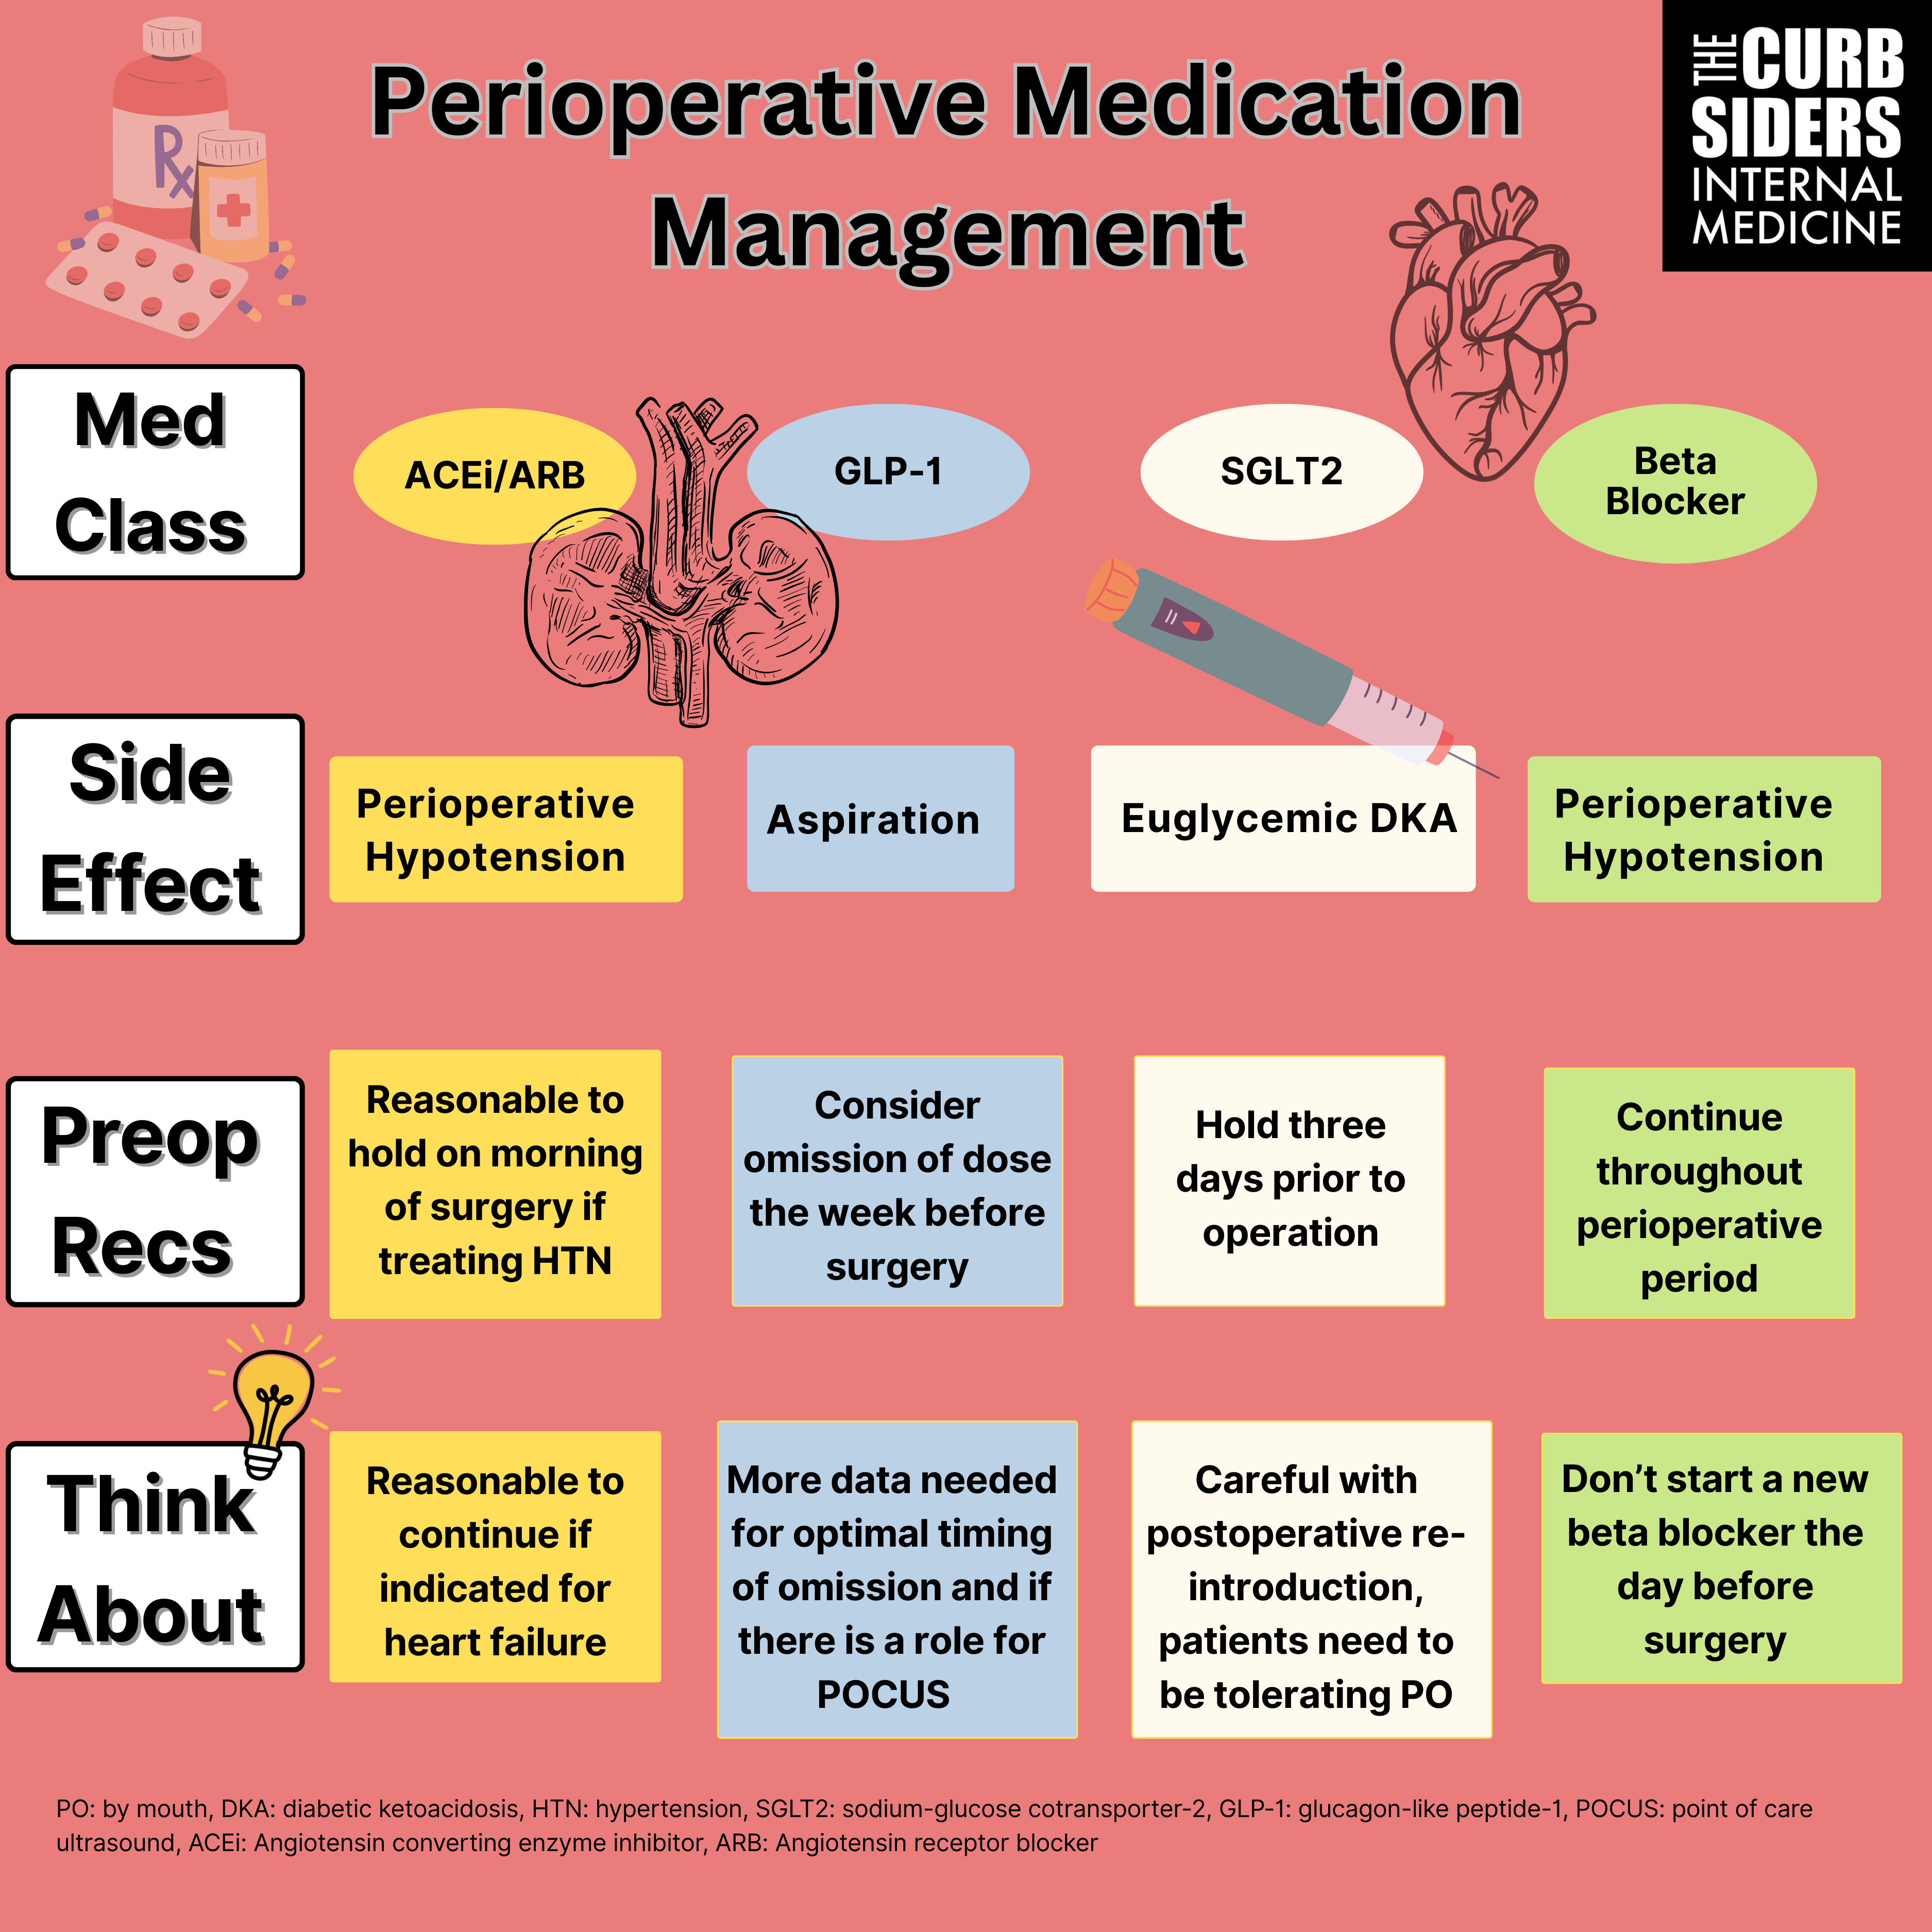
- Cardiac meds: ACE/ARBs – For HFrEF patients, continue (2A); for well-controlled BP and high-risk surgery, consider holding (2B); case-by-case decision-making is key. Beta-blockers should not be started the day before surgery due to the risk of intraoperative hypotension. They should be continued perioperatively if patients are on them chronically, however.
- OSA does not usually require delaying surgery – Instead of sleep studies, which are usually not able to be streamlined before surgery in the US, risk modification (upright sleeping, opioid avoidance, inpatient monitoring) is a reasonable approach.
- Perioperative BP thresholds matter – Surgery is not necessarily canceled for 160s SBP, but if consistently ≥180/110, consider optimization before proceeding.
- Pre-op troponin is helpful if checking post-op. Without a baseline, interpreting post-op elevations is challenging. Myocardial injury after noncardiac surgery (MINS) describes patients with postoperative troponin elevations that are not due to a nonischemic cause (e.g. sepsis).
- BNP/NT-proBNP is a valuable risk stratification tool that helps guide diagnostic uncertainty (e.g., dyspnea, heart failure risk) and serves as a middle ground before stress testing in select patients.
- Frailty reflects physiologic reserve, guiding prehab, post-op expectations, and the decision between invasive vs. less invasive surgery. It is different than disability or comorbidity, although patients may have both.
- NPO after midnight often results from institutional inertia, when in reality patients can safely receive clear liquids up to two hours before surgery. This may actually lead to better outcomes as patients are more hydrated before surgery.
- Diabetes meds: SGLT2 inhibitors should be held for 3 days pre-op to prevent euglycemic DKA. GLP-1 agonists should be omitted the week of surgery, but watch for more data on how to manage these patients in the future.
- Post-op atrial fibrillation (AF) does not automatically require immediate inpatient treatment – Consider CHA2DS2-VASc (or CHA2DS2-VA) risk, underlying triggers, and wearable monitoring (e.g., Apple Watch) before deciding on anticoagulation. Handoff to outpatient providers regarding AF is critical.
Perioperative Update – Show Notes
Preoperative Assessment: Consulting Tips
How Can We Best Support the Surgical Team?
Our role is to give an updated insight into a patient’s healthcare problems in anticipation of surgery. Beyond just the problem list, this means actually evaluating each major medical condition and giving meaningful, evidence-based recommendations to best support the surgeons prior to the operation. For example, if a patient has cirrhosis, the provider should determine the status of that cirrhosis. Is it decompensated? Is there something we can optimize regarding the disease before they go for surgery? (expert opinion, Modha 2022)
Interdepartmental Diplomacy
Surgeons may request specific tests, some of which may not be indicated, but our approach should be thoughtful and collaborative rather than dismissive. If a test is requested, we should diplomatically explore whether it adds value to patient care (expert opinion). Dr. O’Glasser emphasizes the importance of establishing strong working relationships with surgical teams, as this fosters a cooperative environment where decision-making is driven by evidence rather than institutional inertia. Maybe the surgeon saw something in the chart that the PCP did not, and engaging in a collaborative conversation is the best way to move forward on a shared common ground. Avoiding judgmental and dismissive transactions helps build institutional relationships and drives continued progress in this field (expert opinion).
Challenging Low-Value Testing
There are many preoperative tests that add little value to preoperative care yet have persisted (expert opinion). These may include coagulation tests (coags), urinalysis (UA), and other routine labs before low risk surgery (Modha 2022). Studies have repeatedly shown that testing coags before surgery (in the absence of a specific indication) does not improve outcomes (Salar 2014, Chee 2008), yet they are regularly requested by proceduralists. When systemic low-value testing is identified, engaging with the broader surgical group can be beneficial (expert opinion). Asking why a test is being done in a collegial manner can encourage discussions about the evidence behind it and drive systemic improvement. (Harris 2023).
However, It remains essential to prioritize the individual patient in front of you. In cases where additional testing is unlikely to influence immediate clinical decision-making, but delaying surgery may not align with the patient’s best interests, facilitating timely surgery may be the most prudent course of action while simultaneously working toward broader institutional change in the long term (expert opinion).
What Goes in the Chart?
When recommendations are made to the surgery team, the medical documentation should be concise and actionable with a clear message. Dr. O’Glasser mentions a few specific tips for being a helpful consultant in this context, and the note should generally contain:
- Whether the patient is optimized for surgery
- A blurb about each of their relevant conditions (e.g. heart failure appears compensated with no current signs of hypervolemia)
- Additional steps that may be required for full optimization before their procedure
Ultimately, the goal is to provide practical, evidence-based recommendations that maximize the odds of a good outcome (expert opinion, Vazirani 2012).
Understanding Risk Prediction
Perioperative Cardiac Risk Assessment: Choosing the Right Tool
When faced with a patient with risk factors for cardiovascular disease (CVD), the ACC/AHA guidelines contain a helpful algorithm for how to proceed. Risk calculators are used on an early step in the algorithm that may direct the provider towards further testing or straight to surgery, depending on the results. Further testing is indicated either when the risk calculator denotes “elevated risk” (each calculator has its own threshold for this) or when there is a presence of a “risk modifier” (further outlined below). There are essentially three pathways in the algorithm, either the patient has a low calculated risk and no risk modifiers (these can go straight to surgery), or they have either an elevated risk based on the calculator or the presence of a risk modifier (in which case next steps are in part dictated by the patient’s functional status).

The risk modifiers are as follows:
- Severe valvular disease
- Severe pulmonary hypertension
- Elevated risk congenital heart disease
- Prior coronary stents
- Recent stroke
- CIED: Cardiac implantable electronic device (pacemaker/ICD) present
- Frailty
There are several options for risk calculators that can be used, each with their own nuances. Each model is designed to assess specific outcomes based on distinct patient populations and datasets. Understanding these differences is essential for applying them effectively. Rather than using risk calculators as rigid decision-making tools, clinicians should incorporate them into an evidence-based, patient-centered approach. The goal is not only to predict risk but to inform decision-making in perioperative care. Much like a D-dimer in venous thromboembolism evaluation, cardiac risk calculators should be interpreted within the context of a broader clinical assessment rather than in isolation—and, similar to D-dimer testing, their greatest utility often lies in identifying low-risk patients rather than ruling in disease (expert opinion). The 2024 ACC/AHA perioperative guidelines outline several risk calculators that can be used in this setting, including the Revised Cardiac Risk Index (RCRI), Myocardial Infarction and Cardiac Arrest (MICA), ACS NSQIP (American College of Surgeons National Surgical Quality Improvement Program).
RCRI
The RCRI was originally developed to predict major perioperative cardiovascular events, and while it has recently been recalibrated for improved accuracy, its fundamental limitations persist (expert opinion, Vernooji 2021). Using old data sets, the RCRI was suboptimal at predicting postoperative myocardial events given the changing definitions of MI and different cardiac biomarker assays that evolved over the years since the RCRI was initially introduced. The model was recalibrated to include these modern changes; it now uses a score >1 as the key cutoff, removing previous percentage-based thresholds (Thompson 2024). Despite its simplicity and widespread use, RCRI has notable constraints—it underestimates risk in certain surgical populations, particularly vascular surgery patients, and omits key clinical factors such as advanced age, poor functional capacity, or aortic stenosis (Bertges 2010). While useful as a quick screening tool, its limited scope means it should be used cautiously and often supplemented with other risk models to ensure a more comprehensive preoperative cardiac risk assessment (expert opinion).
MICA
The MICA calculator (commonly known as the “Gupta”), developed in 2011, is a more comprehensive risk model than the RCRI, offering improved predictive power for perioperative MI and cardiac arrest (Gupta 2011). Dr. O’Glasser personally prefers the use of this calculator over the RCRI. It was derived from a larger, more diverse cohort and applies a 1% threshold for elevated cardiac risk, making it particularly useful for modern surgical patients (expert opinion, Gupta 2011, Thompson 2024). Compared to RCRI, MICA incorporates additional clinical variables such as the American Society of Anesthesiologists (ASA) class, functional dependence, age, and renal function, leading to improved discrimination for cardiac events, especially in non-cardiac surgery patients (Thompson 2024). However, risk estimates from MICA and other models should always be interpreted within the patient’s overall clinical context (expert opinion).
ACS NSQIP
The ACS NSQIP Surgical Risk Calculator is a widely used, data-driven tool that provides patient-specific risk estimates for postoperative complications based on real-world outcomes from over a million surgical cases (Bilimoria 2013). Unlike traditional preoperative cardiac risk calculators such as the RCRI or MICA, which focus primarily on predicting major adverse cardiovascular events, the NSQIP calculator offers a more comprehensive assessment, estimating risks for multiple complications, including infections, thromboembolic events, and renal failure. It is a real time database that incorporates a broader set of preoperative variables, adjusts for procedure-specific risks, and has been validated across various surgical specialties, making it a valuable complement (although more involved) to cardiac-focused models in preoperative decision-making (Cohen 2013). Consider using this model when taking into account more than just cardiac risk factors (expert opinion).
Other Models
Other validated tools do exist, such as the AUB-HAS2, the Goldman Index, and others. Each has its own strengths and limitations, its own threshold to denote elevated risk, and its own cohort of patients on which it was validated (Thompson 2024).
Frailty as a Risk Modifier in Perioperative Care
Why Does Frailty Matter?
Frailty was a highlighted area of the 2024 ACC/AHA guidelines and should be considered a distinct entity apart from disability or comorbidities. Frailty affects response to surgical stress and postoperative recovery, and identifying it allows for proactive, rather than reactive, management—helping providers mitigate risk rather than simply predicting it (Thompson 2024). Frailty assessment informs key perioperative decisions, including proceeding with or canceling surgery based on risk-benefit considerations, delaying surgery to allow for prehabilitation and optimization, and guiding discussions on the risks and potential benefits of invasive vs. less invasive procedures (e.g., TAVR vs. SAVR) (expert opinion, Thompson 2024).
How Do We Assess Frailty?
Frailty assessments should be patient-centered, multidimensional, and practical. Several validated tools exist, but no single calculator is superior in predicting surgical outcomes. The key is to pick one, get comfortable using it, and apply it consistently (expert opinion, Thompson 2024). The FRAIL Score / Edmonton Frail Scale can be largely completed by the patient and incorporates psychosocial factors. Dr. O’Glasser will also utilize the Mini-Cog to supplement her frailty assessment as this brings in a neurocognitive assessment. Some frailty assessments can be modified for virtual visits (expert opinion). Dr. O’Glasser highlights that eyeballing a patient’s mobility and cognition can offer quick, valuable insights as a simple bedside test.
Frailty screening should lead to actionable interventions rather than just documentation. The conversation should be patient-centered (expert opinion, Walston 2018):
- “What is life like for you now?”
- “How different was it before you were admitted?”
- “How can we get you back to baseline before surgery?”
This shifts the focus from whether surgery is possible to how we optimize the patient for the best possible outcome (expert opinion).
Strategies for Frail Patients Undergoing Surgery
Before surgery, patients can benefit from prehabilitation—a structured approach to building strength and improving function to optimize their recovery. Beyond physical preparation, it is equally important to consider support systems: Who will be there to assist at home? What resources can be mobilized to ease the transition postoperatively?
Providers should equip patients and families with the right expectations. Through anticipatory coaching, they should understand the importance of early mobilization—getting out of bed, transitioning to a chair, and actively participating in physical therapy assessments as soon as possible. Dr. O’Glasser emphasizes that these early efforts can significantly impact outcomes, leading to smoother recoveries and reduced complications (Richards 2018).
What If Frailty Is Irreversible?
There are situations where surgery may not be the best option. In these cases, Dr. O’Glasser recommends a diplomatic and patient-centered approach when communicating with the surgical team. She suggests expressing concerns in a collaborative way, such as stating, “I am concerned about [X] and how it may impact recovery.” By focusing first on modifiable factors, the discussion can shift toward optimizing what can be improved.
Postoperative Considerations
Frailty is not confined to the operating room—postoperative care plays a crucial role in recovery. To support frail patients, early consultation with geriatrics can help optimize post-op management for some patients. Becoming familiar with institutional pathways can be helpful, as hospitals may have specific pathways in place to provide structured care. For patients with substance-use disorders, inpatient addiction medicine involvement can play a helpful role (expert opinion, Richards 2018 Thompson 2024). Ultimately, Dr. O’Glasser reminds the audience that frailty assessment is not about restricting access to surgery; rather, it is about strengthening patient resilience, facilitating informed decision-making, and improving overall outcomes.
Pulmonary Considerations
Obstructive Sleep Apnea
Obstructive sleep apnea (OSA) has long been recognized as an important perioperative risk factor, yet according to Dr. O’Glasser it rarely is a reason to delay or cancel surgery (Fassbender 2016). While screening tools like STOP-BANG help identify high-risk patients, it is impractical to refer everyone with risk factors for OSA to obtain diagnostic testing prior to surgery (expert opinion, Verbraecken 2017). Providers can instead focus on risk mitigating strategies for patients with or at risk for OSA. The approach is often individualized for each patient, but some approaches Dr. O’Glasser considers might be:
- Encouraging side or upright sleeping rather than supine positioning.
- Minimizing opioids at bedtime to reduce the risk of hypoventilation.
- Ensuring appropriate post-op monitoring—patients with moderate-to-severe OSA may benefit from an inpatient stay for closer observation rather than outpatient surgery with same-day discharge (Cozowicz 2021, Gross 2014).
The reality is that many patients have undiagnosed or untreated OSA, and the goal is not to flag patients and stop their surgeries but rather to anticipate complications and adjust care accordingly (expert opinion). While CPAP is the standard treatment, not everyone can tolerate it—and Dr. O’Glasser reminds the audience that there are many procedures after which using CPAP may not be practical (e.g. Nissen fundoplication or sinus surgery).
Pulmonary Function Tests
Pulmonary function tests (PFTs) do not change perioperative management, except for in a few scenarios:
- If the patient has dyspnea of unknown etiology—especially in the setting of planned thoracic surgery.
- If the patient would have obtained them anyway in the outpatient setting.
- If a major lung resection is planned (e.g., wedge resection, lobectomy).
Outside of these scenarios, routine PFTs add little value. If a patient’s clinical history and exam suggest adequate pulmonary reserve, additional testing is unlikely to change the plan (Yokota 2020, Mori 2019, Modha 2022).
Pulmonary Hypertension
Pulmonary hypertension (PH) adds an extra layer of complexity to most surgeries, given the physiologic impact of PH on right ventricular function and overall hemodynamic stability, which requires careful consideration and coordination from specialists and anesthesia on appropriate intraoperative monitoring and vasoactive support, and to ensure any potential PH therapy is maximized before surgery (Olsson 2018).
Perioperative Medication Management
Renin-Angiotensin-Aldosterone System (RAAS) Inhibitors
RAAS inhibitors namely angiotensin converting enzyme inhibitors (ACEi) and angiotensin receptor blockers (ARB) have long been a point of contention in the perioperative setting. These vasodilatory agents can contribute to sustained intraoperative hypotension (Thompson 2024), but does that actually translate to worse outcomes postoperatively? The answer is not entirely clear.
Prospective RCTs, including the SPACE trial, suggest that while prolonged intraoperative hypotension is more common when ACEi/ARBs are continued, it may not meaningfully impact post-op outcomes (Ackland 2024). Thus, in many cases, deciding whether to hold or continue these medications feels like flipping a coin—the risks of hypertension and hypotension seem to cancel each other out (expert opinion).
Current Guidelines: Case-by-Case Approach
The 2024 ACC/AHA guidelines offer a nuanced take:
- Class 2A: It is reasonable to continue ACEi/ARB therapy in patients with heart failure with reduced ejection fraction (HFrEF).
- Class 2B: Consider holding in certain patients, particularly those with well-controlled BP undergoing high-risk surgery.
If hypertension is uncontrolled, keeping the ACEi/ARB may be beneficial. If BP is well-controlled and surgery is high-risk, holding the medication may help avoid hypotension-related complications (Thompson 2024).
BP Threshold for Surgery — Insider Tips
There is no absolute BP cutoff for proceeding with elective surgery, but Dr. O’Glasser suggests a reasonable approach:
- Most patients with poorly-controlled hypertension: Continuing ACEi/ARB is fine (expert opinion).
- Patients with significant CV risk factors and very poorly controlled BP (≥180/110): Deferring surgery may be reasonable to avoid complications.
- A patient sitting at 130-140 mmHg in the pre-op clinic? Perfectly fine for a clinic measurement, proceed to surgery (expert opinion).
- A patient at 160 mmHg in clinic but obviously stressed? Document it as an outlier provided home readings look controlled.
- A patient running 180-190 mmHg consistently? That is a different story—this might be a case of medication nonadherence, or therapy may need to be optimized preoperatively—consider adjusting doses or adding another agent if adherence has been adequate (expert opinion).
- Encourage home monitoring: goal 130/80 for most patients (Flack 2020).
Remember to treat the individual patient, there is no one-size fits all rule for every scenario (expert opinion).
SGLT2 Inhibitors and Loop Diuretics
For patients on SGLT2 inhibitors (e.g., Empagliflozin, Dapagliflozin) it is best to hold three days before surgery to reduce the risk of perioperative euglycemic DKA (Thompson 2024).
For fragile CHF patients, continue loop diuretics up until the morning of surgery. Hold SGLT2 inhibitors but have a PRN plan for diuresis if volume overload is a concern (expert opinion, (Thompson 2024).
GLP-1s
With the rise of GLP-1 receptor agonists (e.g., Tirzepatide, Semaglutide), there is growing concern about delayed gastric emptying and potential aspiration risk perioperatively. While much of this remains theoretical, current best practices suggest holding GLP-1 medications for at least a week before surgery (Ushakumari 2024). Some have proposed gastric ultrasound (POCUS) to assess gastric contents, but reliability and practicality remain uncertain (expert opinion, Jalleh 2024).
NPO at Midnight: Inertia or Evidence?
Why Are We Still Doing This?
The traditional “NPO after midnight” rule is one of those things providers do more out of habit than necessity. “Things We Do for No Reason™: NPO After Midnight” is an article that highlights these points; institutional inertia has kept this practice alive far longer than the data supports (Black 2021). Fortunately, the guidelines from the American Society of Anesthesiologists (ASA) have evolved, now acknowledging that clear liquids up to two hours before surgery are safe and beneficial (Joshi 2023).
The simple rule? If you can hold it up to the light and read through it, it is a clear liquid (Oates 2023).
- Okay: Water, black coffee, cranberry juice, clear sodas (Sprite, ginger ale).
- Not okay: Fruit juice with pulp, milk-based drinks, kombucha.
The Science Behind It: Faster Gastric Emptying, Better Outcomes
Data overwhelmingly supports that gastric emptying is fast enough to allow clear liquids up to two hours before surgery without increasing aspiration risk. The benefit is that patients come into surgery more hydrated and less physiologically stressed. Liberalized NPO policies align with ERAS (Enhanced Recovery After Surgery) protocols, which have been widely shown to improve surgical outcomes (Melynk 2011). Even for major surgeries like a Whipple procedure, some centers now allow a carbohydrate-rich sports drink preoperatively to improve perioperative metabolism and reduce insulin resistance (expert opinion, Ljungqvist 2017).
Perioperative Biomarkers: When Do They Matter?
Brain Natriuretic Peptide (BNP) and N-Terminal Pro-B-Type Natriuretic Peptide (NT-proBNP)
In certain patients at elevated risk for CVD, with poor or unknown functional status, measuring preoperative BNP or NT-proBNP is a 2a recommendation in the guidelines (Thompson 2024). This positions it as a tool to engage in clinical reasoning about a patient’s baseline cardiovascular function. The trick is knowing when to use it and how to interpret it in context. In cases of diagnostic uncertainty (e.g., dyspnea with unclear JVP findings), BNP or NT-proBNP can fill the gap between clinical assessment and more invasive testing. It can also serve as a middle ground before deciding on a pre-op stress test—if BNP is very elevated, it may suggest underlying cardiac disease that warrants further evaluation (Thompson 2024).
Perioperative Troponin
The 2024 ACC/AHA guidelines currently give a 2b recommendation to measuring preoperative troponin in patients with poor or unknown functional status undergoing elevated risk surgery, but also those over the of 65 or with risk factors for CVD (Thompson 2024). Without a preoperative troponin, it is impossible to know whether an elevated value is truly new or simply a chronic baseline abnormality, particularly in ESRD patients who may have chronically elevated troponin levels due to impaired renal clearance of troponin and a low degree myocardial injury. The Canadian and European guidelines have emphasized that if providers are going to check a post-op troponin, it may be beneficial to check a pre-op troponin as well—not necessarily because it changes the surgical plan, but because it helps interpret post-op results and avoid unnecessary cardiac workups (Duceppe 2017, Halvorsen 2022).
However, Dr. O’Glasser mentions that this is a new recommendation and many institutions may not be set up to handle routine troponin testing in asymptomatic patients, and there is not great data on what to do with the elevations if they are found, aside from aggressive risk factor modification. As institutions develop the resources and the local guidelines to handle this, then checking perioperative troponins might become more of a routine practice in select patients. But for now, this is not something that is widely practiced in the United States (expert opinion). Remember, this is referring to checking asymptomatic troponins as a risk assessment; if the patient has symptoms, that becomes a different pathway and is not what is referred to here.
Myocardial Injury after Noncardiac Surgery (MINS): What Do We Do With Postoperative Troponin Elevations?
MINS: Definitions
Myocardial Injury After Non-Cardiac Surgery (MINS) is a recognized predictor of poor post-op outcomes, but defining it is tricky. According to the AHA scientific statement, to count as MINS upfront, the patient must have:
- Elevated postoperative high-sensitivity cardiac troponin (HS-cTn) with at least one measurement above the 99th percentile of the URL, showing a rise/fall pattern indicative of acute myocardial injury. This is technically a ≥20% HS-cTn rise after surgery, an absolute increase in HS-cTn troponin of ≥14 ng/L above preoperative values, or an increase of ≥5 ng/L above the prior concentration and with a peak HS-cTn >20 ng/L (Ruetzler 2021).
- Occurs within the first 30 days after surgery, typically within 72 hours.
- Attributable to a presumed ischemic mechanism (e.g., supply-demand mismatch or atherothrombosis) without an overt nonischemic cause (e.g., sepsis, pulmonary embolism).
- Ischemic symptoms or ECG changes are not required, as symptoms may be masked by perioperative sedation or analgesia (Ruetzler 2021).
MINS is an overarching term to describe any postoperative HS-cTn elevation, except those caused by nonischemic conditions like sepsis and PE. The various causes of troponin elevations can then be further broken down into their respective entities:
- ST-elevation myocardial infarction (STEMI)
- Non-ST-segment myocardial infarction (NSTEMI) — both type one (plaque rupture) and type two (supply-demand mismatch)
- Nonischemic myocardial injury (the only one on this list that is not “MINS”)
- Myocardial injury —does not meet fourth universal definition of MI, so this one is “true MINS” and is not managed like the above syndromes. For the purpose of the rest of this section, MINS will refer to this entity which is essentially asymptomatic troponin elevations after surgery.
Note: the first two (STEMI and NSTEMI) meet the fourth universal definition of MI, defined as a rise and/or fall of cardiac troponin values with at least one value above the 99th percentile, along with at least one additional indicator of ischemia—such as symptoms of chest pain, ischemic electrocardiographic changes, development of pathological Q waves, imaging evidence of new myocardial damage, or confirmation of a coronary thrombus via angiography or autopsy. STEMI and NSTEMI should be managed according to guidelines for those entities. Non-ischemic myocardial injury should be treated by addressing the underlying cause (Ruetzler 2021).
MINS: Management
It is not entirely clear what to do about incidental MINS, but many patients have underlying obstructive coronary disease that was never addressed before surgery. A study from nearly a decade ago showed alarmingly low rates of risk factor modification in these patients (Chen 2019). Thus, at the very least, Dr. O’Glasser emphasizes that this should be an added reason to emphasize aggressive risk factor modification. Smoking cessation, glycemic control, blood pressure optimization, and other risk reduction is paramount in these patients (Ruetzler 2021). Some observational data suggest those on aspirin and a statin do better (Devereux 2011, Thompson 2024) but this can be individualized; many may have indications for statins and / or aspirin already. The MANAGE trial looked at starting patients with MINS on dabigatran, and while patients did better on average, the composite outcomes were likely driven by clot reduction rather than major adverse cardiac events. As of now, starting dabigatran is not a widespread practice, but in the future, more people may be put on dabigatran or other DOACs (expert opinion, Ruetzler 2021 Devereaux 2018, Thompson 2024).
Remember, discovering MINS opens the door for a teachable moment—a warm handoff to primary care is crucial. Involving cardiology in these decisions may lead to better outcomes, so know your institutional patterns and pathways (expert opinion, Ruetzler 2021).
Atrial Fibrillation (AF) in the Perioperative Period
AF Before Surgery
AF is common perioperatively and often does not require an immediate, aggressive intervention. Instead, the key is paying attention to the details. If the AF is rate-controlled and the patient asymptomatic, it may be reasonable to proceed with time-sensitive surgery without postponing or cancelling (expert opinion). If the AF suggests an underlying condition, think about a basic workup including BNP/NT-proBNP, complete blood count (CBC), metabolic panel, thyroid stimulating hormone (TSH), and STOP-BANG (OSA) among potential other tests that may be indicated (Joglar 2024).
A preoperative echocardiogram before noncardiac surgery in the setting of new onset AF should probably only be pursued before surgery if it is likely to change management (expert opinion). If the patient is stable and rate-controlled, it is often unnecessary to obtain before the surgery, but it would still be indicated as part of the new AF workup (Joglar 2024). However, if the planned surgery is highly invasive, or if there are any confounding factors, reconsidering the approach may be warranted (expert opinion).
Beta-Blockers
New guidelines reinforce that beta-blockers should not be started the day before surgery—a strategy that was once common but has been shown to carry a risk of intraoperative hypotension without proven benefit (Thompson 2024). If patients are on them chronically before surgery, then continue them uninterrupted throughout the perioperative period.
Postoperative AF
The management of post-op AF is analogous to post-op troponin elevations—we recognize that it is a marker of stress rather than necessarily a standalone disease (Thompson 2024). Surveillance matters, but we may be able to simply monitor patients who develop brief perioperative AF in the hospital, especially if they resolve. That being said, these patients need to be counseled on the risk of recurrence and they should have a plan in place to handoff care to the follow-up provider, as they will need close monitoring. A CHA2DS2-VASc (or CHA2DS2-VA) approach is useful, as post-op AF should be thought about like other forms of AF in terms of stroke risk (Lip 2024). Wearable monitoring (Apple Watch, Kardia, etc.) or cardiac event monitors should be employed to help patients track any ongoing AF after discharge.
As with MINS, postoperative AF is often a harbinger of underlying disease rather than acute, isolated events. Addressing risk factors and monitoring for recurrence in the long term is more meaningful than an aggressive, knee-jerk reaction in the immediate perioperative window.
Links
- Things We Do for No Reason™: NPO After Midnight
- MICA (Gupta) Risk Calculator
- Edmonton Frail Scale
- FRAIL Scale
Goal
Listeners will familiarize themselves with the latest perioperative medicine guidelines.
Learning objectives
After listening to this episode listeners will…
- Discuss updates to the most recent (2024) ACC/AHA guidelines on the management of perioperative care and how they differ from past guidelines
- Recognize the limitations of modern cardiac risk calculators and how these calculators should be used in clinical practice
- Identify how cardiac biomarkers and stress testing should be used to drive decision-making in perioperative patients before and after surgery.
- Discuss how pulmonary conditions such as obstructive sleep apnea impact perioperative care
- Discuss best practices of perioperative consultation including medications, labs, and how to best communicate your recommendations to the surgical service
Citation
Wurtz PJ, O’Glasser AY, Williams PN, Watto MF. “#475 Perioperative Update with Dr. Avital O’Glasser”. The Curbsiders Internal Medicine Podcast. thecurbsiders.com/category/curbsiders-podcast March 17, 2025.
Episode Sponsors
EZResus
Listeners of the Cribsiders and Curbsiders podcasts get access to a 2-month free trial,letting them use 100% of the features of the
For more information, www.ezresus.com/curbsiders and Use promo code Curbsiders
Freed
Visit Freed.ai and Usecode:CURB50 to get $50 off your first month when you subscribe.
Mint Mobile
Get 3 months of premium wireless service from Mint Mobile for $15 a month. Shop plans at mintmobile.com/curb
Episode Credits
Written and produced, show notes, cover art, CME, and infographics: Paul Wurtz MD.
Hosts: Matthew Watto MD, FACP; Paul Williams MD, FACP
Reviewer: Molly Heublein MD
Showrunners: Matthew Watto MD, FACP; Paul Williams MD, FACP
Technical Production: PodPaste
Guest: Avital O’Glasser MD
CME Partner

The Curbsiders are partnering with VCU Health Continuing Education to offer continuing education credits for physicians and other healthcare professionals. Visit curbsiders.vcuhealth.org and search for this episode to claim credit.
Contact Us
Got feedback? Suggest a Curbsiders topic. Recommend a guest. Tell us what you think.
We love hearing from you.
Join our Patreon!

Yes, you can now join our exclusive community of core faculty at Kashlak Memorial Hospital along with all the perks:
- Bundle & Save with the top CME tier!
- All episodes Ad-Free, including the entire back catalog!
- Twice-monthly bonus episodes: Ask me Anything (AMA) with Matt & Paul, Recaps, and more!
- Access to Kashlak's Discord Server!
- Advance Notice of Curbsiders Events!
- Exclusive Curbsiders' Merch!
